
Daily-to-Weekly GLP-1 Questions Clinician Discussion Guide


THE BOTTOM LINE
Clinically, switching from Saxenda (liraglutide) to Mounjaro (tirzepatide) is a transition from a daily single-receptor agonist to a weekly dual-receptor agonist. Because these medications utilize different biological mechanisms and have vastly different half-lives, there is no direct milligram-to-milligram conversion.1
The standard medical care plan discussion requires patients to discontinue Saxenda, observe a 24 to 48-hour washout period, and restart Mounjaro at the lowest initiation dose (2.5 mg) to avoid acute gastrointestinal distress. Do not stack medications.1
What This Switching Review Covers
- Why A Daily Saxenda Dose Does Not Translate To A Mounjaro Dose
- How The Reset And Titration Process Usually Works
- What Side Effects Can Reappear During The Transition
- What To Clarify With Your Prescriber Before You Switch
The Biology: Why You Can't Just "Swap" Doses
To understand why the treatment planning schedule changes so drastically, we have to look at the chemistry. Saxenda (liraglutide) is what we call a selective GLP-1 receptor agonist.1 It mimics one specific hormone, glucagon-like peptide-1, to slow down your stomach emptying and send "fullness" signals to your brain.1 It’s a workhorse, but it has a very short half-life of approximately 13 hours.1 That’s why you have to inject it every single day; if you miss a dose, the medicine is effectively gone from your system within 24 hours.2
Mounjaro (tirzepatide) represents a generational leap in metabolic medicine: the Twincretin.1 It is a single molecule that acts as a dual agonist.1 It binds to the GLP-1 receptor plus the GIP (glucose-dependent insulinotropic polypeptide) receptor.1, 2

The "Twincretin" Advantage
While GLP-1 focuses on appetite suppression, the GIP component is believed to act directly on adipose (fat) tissue and improve insulin sensitivity. This synergistic effect is why Mounjaro often shows higher efficacy in clinical trials (up to 20.9% weight loss in SURMOUNT-1) compared to single-agonist injections.1
However, because Mounjaro binds more aggressively to these receptors, the transition must be managed carefully.1, 3 If you introduce this new GIP signal too quickly, you risk "receptor overload," which manifests as severe nausea, projectile vomiting, and dehydration.1, 3
Start Quiz
Find your best GLP-1 match
Where should compare start?
Changing treatment next?
Compare switching support
Coach Claire says:
Thinking about trading in your daily Saxenda routine for the weekly freedom of Mounjaro? You are definitely not alone. Making the jump from "daily pokes" to a "once-a-week" shot feels like a massive victory, and it is!
But hold up…we aren't just swapping one pen for another; we are changing the way your biology handles hunger.1 If the first two weeks feel a little different, or if you feel a tiny bit more hungry than usual, do NOT panic.
You're in the "transition zone," and your new routine is about to pay off. Let's look at exactly how to do this safely so you can protect your progress.
The Washout and The "Hunger Gap"
One of the most critical aspects of this switch—and the part most patients are unprepared for—is understanding Pharmacokinetics (PK), or how the drug moves through your body over time.
The "Lag Time" Warning
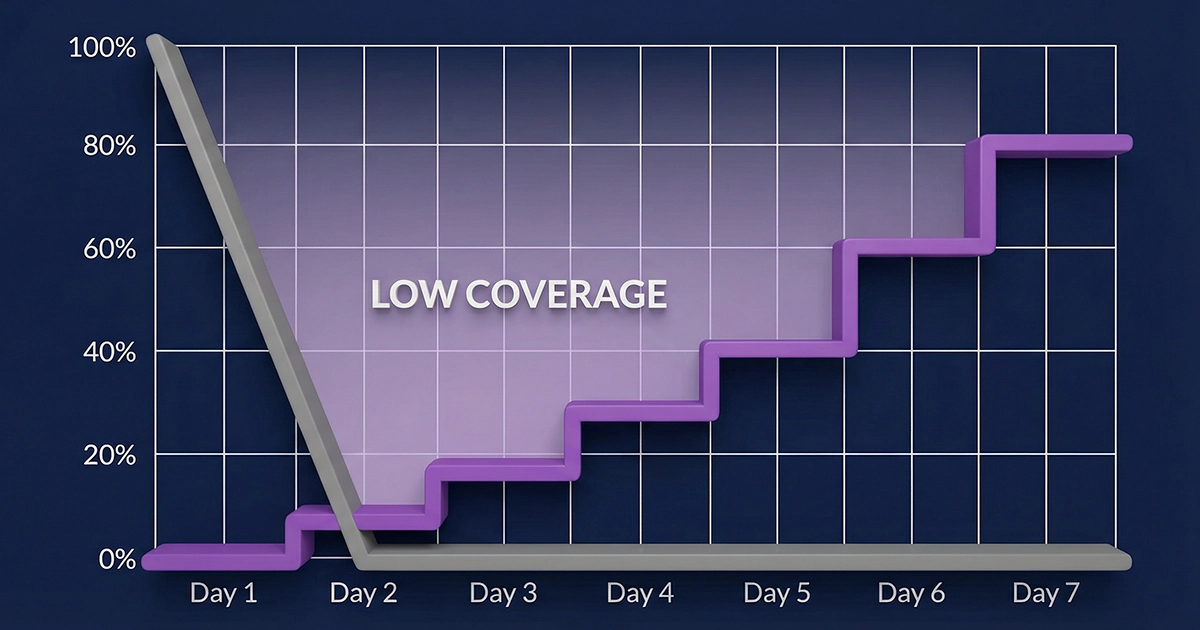
Because Saxenda leaves your system so quickly (within 24 to 48 hours), you lose your "coverage" almost immediately after stopping. In contrast, Mounjaro has a half-life of 5 days, but it takes approximately 4 weeks of weekly treatment planning to build to "steady-state" in your plasma.1
This creates a phenomenon we call the "Hunger Gap."1
- Days 1–7 of the Switch: Your Saxenda is gone. Your first dose of Mounjaro (2.5 mg) is in your system, but it hasn't built up to therapeutic levels yet.
- The Result: You may experience a recurrence of "food noise," cravings, or hunger cues during this window.1
Many patients panic here, thinking the new medication "isn't working."1 This is false. The medication is working exactly as intended; it just hasn't accumulated in your blood yet.1 Do not double your dose to compensate. This is a temporary gap that will close as the tirzepatide accumulates in your system over the first month.1, 4
SAFETY WARNING: The "Stacking" Myth
The Myth: "I have three days of Saxenda left.4 I’ll just use them while I start my Mounjaro so I don't get hungry."
The Clinical Reality: This is a high-risk practice known as "stacking."1 Combining a daily GLP-1 with a long-acting dual agonist can paralyze the stomach muscle, leading to Gastroparesis (stomach paralysis).1 This condition can cause intractable vomiting and may require emergency hospitalization for rehydration.
The Ask your clinician about: Always wait at least 24 hours (and ideally 48 hours) after your last Saxenda injection before administering Mounjaro.4
The Treatment Planning Ask your clinician about: The "Reset" Rule
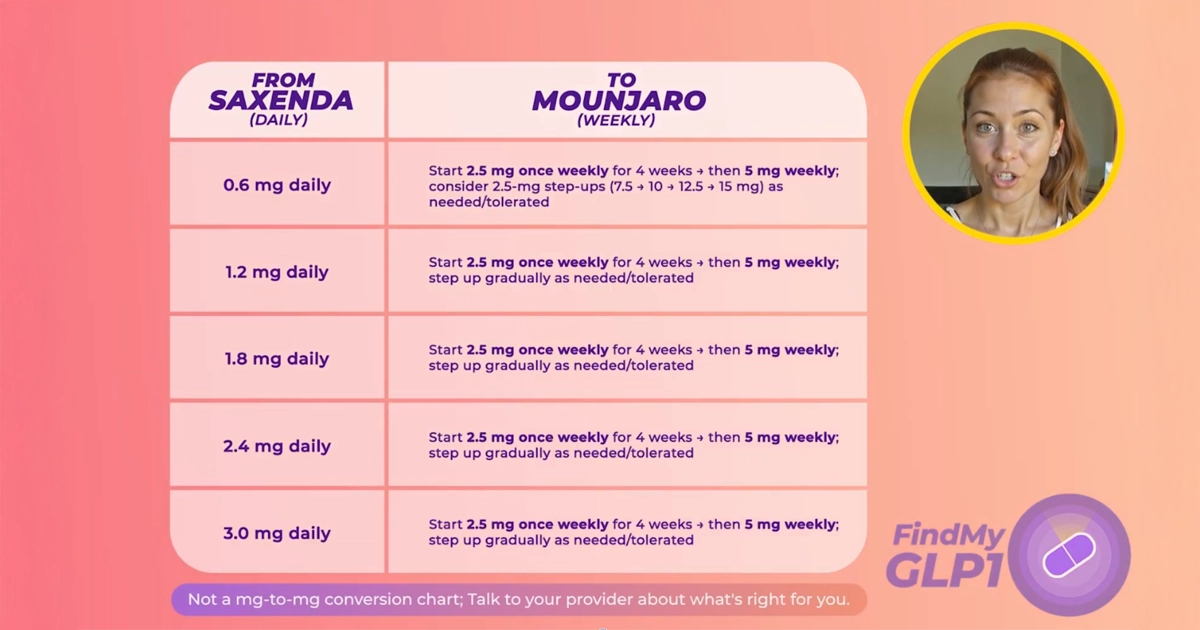
The most common friction point for patients is the dosage reset. Patients who have been on the maximum dose of Saxenda (3.0 mg) for months often expect to start at a medium or high dose of Mounjaro (e.g., 5.0 mg or 7.5 mg).
However, current clinical consensus and manufacturer guidelines dictate that all patients should start Mounjaro at 2.5 mg, regardless of their prior Saxenda dosage.1
Why reset to the bottom?
Because Mounjaro introduces a new mechanism (GIP agonism), your gastrointestinal tract is "naïve" to this specific stimulation. Starting higher than 2.5 mg significantly increases the risk of adverse events, specifically severe diarrhea and abdominal pain that mimics pancreatitis.1
The Standard Switch Schedule
This is the "Stop-Gap-Start" care plan discussion used by most obesity medicine specialists:
- Stop Saxenda: Administer your final daily dose of Liraglutide.
- The Washout: Wait 24 to 48 hours. (Example: If you take Saxenda on Monday morning, do not take anything Tuesday. Take your first Mounjaro Wednesday morning).
- Week 1-4 (Initiation): Inject Mounjaro 2.5 mg once weekly. This is a "loading dose" to get your body used to the GIP hormone.1
- Week 5 (Titration): If tolerated, your provider will likely increase you to 5.0 mg once weekly.1 This is considered the first "therapeutic" dose for many patients.1
Managing Side Effects During the Transition
Because tirzepatide has a longer half-life than liraglutide, side effects can last longer.1 If you injected Saxenda and felt sick, the feeling often subsided by the next morning because the drug was leaving your system. With Mounjaro, if you have a bad reaction, the drug remains active for nearly a week.1
Common Transition Symptoms
- Delayed Nausea: Unlike Saxenda, which hits quickly, Mounjaro nausea often peaks 24–48 hours after the weekly shot.1
- Sulfur Burps: This is caused by significant delayed gastric emptying.1 Food sits in the stomach longer, fermenting and releasing sulfur gas.1
- Constipation: Due to slower bowel motility and potentially lower fluid intake if you are feeling nauseous.1
The "Soft GI" Diet Care plan discussion
To minimize these risks during your first month of Mounjaro, adopt a "Soft GI Diet" for the 24 hours before and after your injection:
Avoid: Raw fibrous vegetables (kale, broccoli), high-fat meats, fried foods, and carbonated beverages.
Embrace: Protein shakes, bone broth, scrambled eggs, and hydration.1
Hydration Goal: Aim for 80–100 oz of water daily. Dehydration is the number one cause of hospitalization for GLP-1 patients.1, 4

Understanding Reviews and Off-Label Use
When switching, you may encounter confusion regarding brand names. It is vital to know exactly what you are taking.
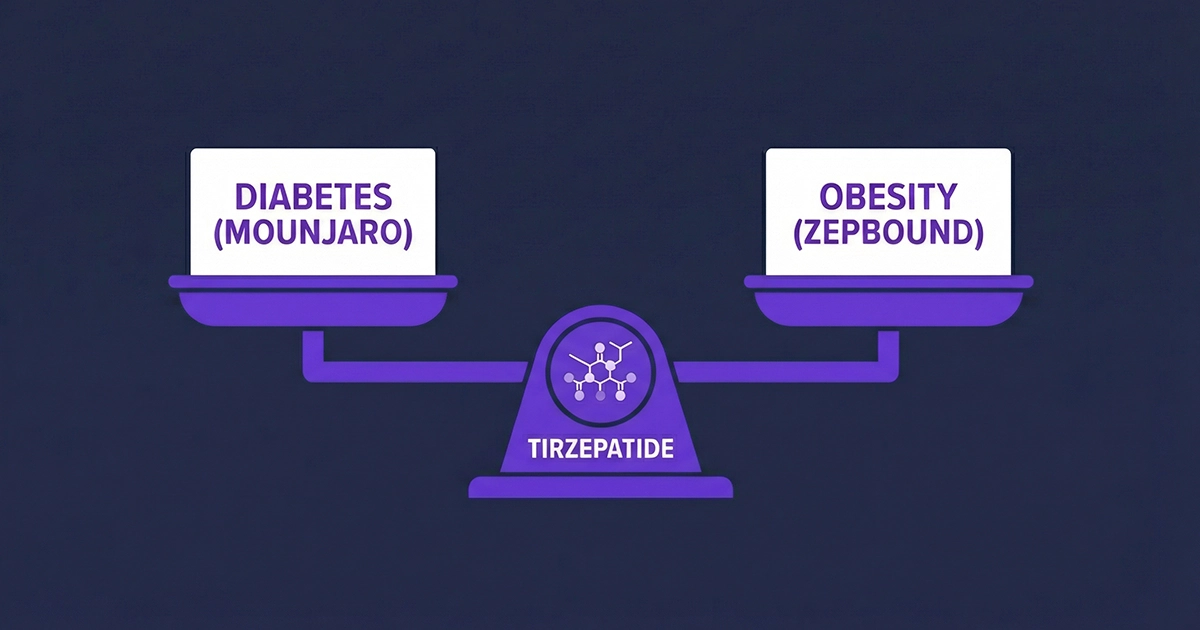
If your doctor prescribes Mounjaro for weight loss (when you do not have diabetes), this is considered "Off-Label" use.1 While this is a legal and common medical practice, your insurance may deny coverage for Mounjaro but approve Zepbound, even though they are the exact same molecule. Always check your formulary before heading to the pharmacy.5
⚠️ CRITICAL: When to Call Your Doctor
While mild nausea is expected, certain symptoms require immediate medical attention.
- Severe Abdominal Pain: Pain that radiates from the stomach to the back (a sign of pancreatitis).1
- Inability to keep liquids down: If you are vomiting for more than 24 hours, you risk acute kidney injury.1
- Hypoglycemia: If you are also taking insulin or sulfonylureas, switching to Mounjaro can cause dangerous drops in blood sugar.1 Your doctor may need to lower your insulin dose before you switch.1, 5
Coach Claire Wrap-Up
You've got the plan, and you know the science. The most important thing to remember is that this switch is a marathon, not a sprint. The scale might not move much in those first few weeks of the 2.5 mg dose, and that is perfectly okay. We are resetting your system for a much bigger win down the road.
Respect the washout period, don't fear the "Hunger Gap," and give your body that full month to adjust to its new weekly rhythm. You're doing great—keep hydrating!
Frequently Asked Questions
How long do I wait to switch from Saxenda to Mounjaro?
The standard care plan discussion requires a 24 to 48-hour washout period. For example, if you take your last Saxenda dose on Monday, wait until Wednesday to inject your first Mounjaro dose.
What starting dose of Mounjaro should I take?
Clinical guidelines dictate starting at the lowest dose of 2.5 mg, regardless of your previous Saxenda dosage, to avoid severe gastrointestinal distress.
Can I use my leftover Saxenda while starting Mounjaro?
No. Do not stack medications. Combining these drugs can cause stomach paralysis (gastroparesis) and severe vomiting.
Is Mounjaro the same as Zepbound?
Yes, they contain the exact same molecule (tirzepatide). Mounjaro is FDA-reviewed for Type 2 Diabetes, while Zepbound is reviewed for chronic weight management.
Coach Claire's Cheat Sheet
Quick definitions used in this article.
References
- Eli Lilly and Company. Mounjaro (tirzepatide) Injection Prescribing Information. Drugs@FDA. 2022. View Source [top]
- Novo Nordisk Inc. Saxenda (liraglutide) Injection Prescribing Information. Drugs@FDA. 2014. View Source [top]
- Jastreboff AM, Aronne LJ, Ahmad NN, et al. Tirzepatide Once Weekly for the Treatment of Obesity. New England Journal of Medicine. 2022;387:205-216. View Source [top]
- Gorgojo-Martínez JJ, et al. Clinical Recommendations for the Management of Patients with Type 2 Diabetes and Obesity Switching from Daily GLP-1 RAs to Weekly Semaglutide or Tirzepatide. Journal of Clinical Medicine. 2023;12(5):1920. View Source [top]
- FDA. Medications Containing Semaglutide Marketed for Type 2 Diabetes or Weight Loss. FDA Safety Communications. 2024. View Source [top]
- FDA. Mounjaro Review History. Drugs@FDA. View Source [top]
- ClinicalTrials.gov. SURMOUNT-1 Trial Results. View Source [top]
- American Diabetes Association. Standards of Care in Diabetes—2023. View Source [top]